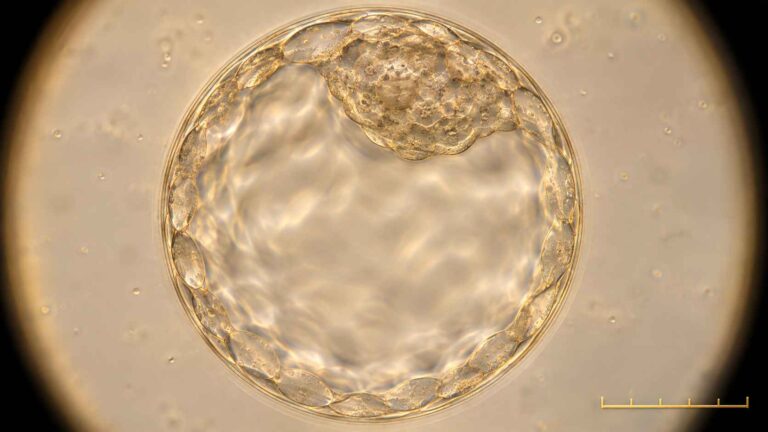
Blastocyst grading is one of the most frequent judgements an embryologist makes. Each day, grades guide decisions on which embryo to transfer, which to cryopreserve and which to keep in culture. Because so much depends on them, grades are only useful when they are applied consistently, recorded clearly and understood for what they are: a structured description of morphology, not a guarantee of outcome.
The three components of a blastocyst grade
Most laboratories use a scoring system derived from the one described by Gardner and Schoolcraft, which records three features of the blastocyst.
1. Expansion and hatching status
A number from 1 to 6 describes how far the blastocoel cavity has developed, from an early blastocyst with a small cavity to a fully expanded, hatching or hatched blastocyst. Expansion reflects developmental progress at the time of observation, so the time of assessment (hours post-insemination) should always be recorded alongside the grade.
2. Inner cell mass (ICM)
The ICM gives rise to the fetus. It is usually graded A, B or C: a prominent, tightly packed cluster of many cells; a looser group of several cells; or very few cells. ICM assessment can be difficult when the embryo is collapsed or the ICM lies out of the focal plane, so the embryo should be viewed at several focal levels before a grade is assigned.
3. Trophectoderm (TE)
The TE forms the placenta and is also graded A, B or C, from many cells forming a cohesive epithelium to very few, large cells. Several studies have associated TE quality with implantation potential, which is why many laboratories give it weight when ranking embryos of similar expansion.
Grading, ranking and selection are not the same thing
The 2025 update of the ESHRE/ALPHA Istanbul consensus distinguishes between grading (describing an embryo), ranking (ordering embryos within a cohort) and selection (the final clinical choice, which also considers patient factors). Keeping these steps separate helps teams avoid over-interpreting a single letter or number.
Practical tips for consistent grading
- Assess at standard times. Agree fixed observation windows for day 5 and day 6 assessments and record the exact time.
- Use reference images. A laboratory atlas with local examples of each grade reduces drift between embryologists.
- Minimise time out of the incubator. Plan assessments in batches so dishes spend as little time as possible outside stable culture conditions.
- Audit inter-observer agreement. Periodically ask several embryologists to grade the same set of images and review disagreements together.
- Document collapsed embryos. Note collapse and re-assess later rather than assigning a low grade straight away.
What grading cannot tell you
Morphology is associated with outcome across large groups of embryos, but it cannot predict the result for an individual embryo with certainty. Embryos with lower grades can lead to healthy live births, and top-graded embryos do not always implant. Clear communication of this limitation to clinicians and patients is part of good laboratory practice.
Key takeaways
- A blastocyst grade combines expansion (1–6), inner cell mass (A–C) and trophectoderm (A–C).
- Always record the time of assessment with the grade.
- Grading, ranking and selection are separate steps, as the updated Istanbul consensus emphasises.
- Regular inter-observer audits keep grading consistent across the team.
Educational content only. This article does not replace institutional protocols, manufacturer instructions, clinical judgement or local regulatory requirements.
References and further reading
- Gardner DK, Schoolcraft WB. In vitro culture of human blastocysts. In: Jansen R, Mortimer D, eds. Towards Reproductive Certainty. Parthenon Publishing; 1999.
- ESHRE/ALPHA working group. The Istanbul consensus update: a revised ESHRE/ALPHA consensus on oocyte and embryo static and dynamic morphological assessment. Human Reproduction. 2025;40(6):989.
- Alpha Scientists in Reproductive Medicine and ESHRE Special Interest Group of Embryology. The Istanbul consensus workshop on embryo assessment. Human Reproduction. 2011.