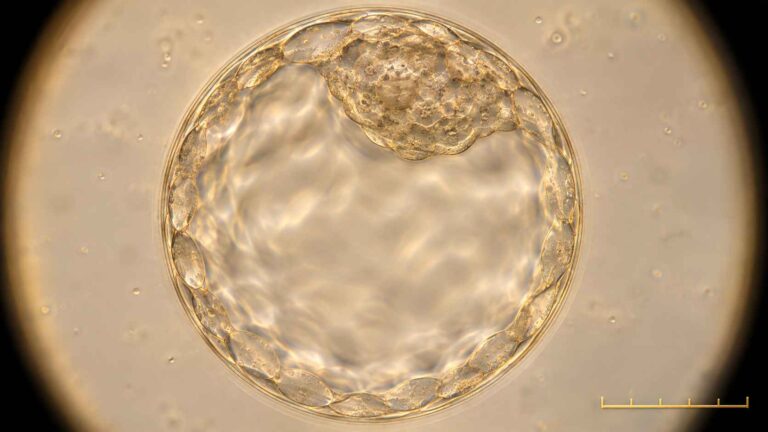
Embryo transfer is the moment where weeks of clinical and laboratory work come together in a few minutes. While the clinician performs the transfer, the embryologist is responsible for the right embryo, correctly loaded, delivered at the right time and confirmed afterwards. Small details in this workflow can make a real difference.
Before the transfer: preparation and identification
- Confirm the plan with the clinician: number of embryos, embryo identity and any patient-specific instructions.
- Witness every step. Patient identity, dish labels and embryo identity should be double-checked by a second person or an electronic witnessing system.
- Prepare equipment in advance. Catheters, syringes and media should be ready and equilibrated so the embryo spends minimal time outside the incubator.
Loading the catheter
Laboratories use different loading techniques, for example with or without small air brackets around the medium column containing the embryo. Published evidence comparing techniques is limited, so the priority is a written, standardised method that every embryologist follows in the same way. Whatever method is used, the volume should be small, the embryo’s position in the catheter known, and loading done smoothly to avoid bubbles that are not part of the protocol.
During the transfer: communication
Clear verbal handover between embryologist and clinician reduces errors. Agree in advance who holds the syringe, how the clinician signals readiness, and how the catheter is returned to the laboratory. Time from loading to deposition should be kept short and recorded.
After the transfer: checking the catheter
The catheter should be flushed and examined under the microscope to confirm the embryo is not retained. If an embryo is found, the laboratory should follow a pre-agreed protocol for immediate re-loading and re-transfer, and the event should be documented and reviewed. Tracking how often retained embryos occur is a useful quality indicator.
Building a safer workflow
- Write a step-by-step SOP covering preparation, loading, handover and post-transfer inspection.
- Train and assess every embryologist against the SOP.
- Record key times (out of incubator, loaded, transferred) for every procedure.
- Review incidents such as retained embryos or difficult transfers together with the clinical team.
Key takeaways
- Embryo transfer is a team procedure with clear laboratory responsibilities.
- Witnessing and identification checks are non-negotiable.
- A standardised loading technique matters more than which technique is chosen.
- Always inspect the catheter after transfer and document any retained embryo.
Educational content only. This article does not replace institutional protocols, manufacturer instructions, clinical judgement or local regulatory requirements.
References and further reading
- ESHRE Guideline Group on Good Practice in IVF Labs. Revised guidelines for good practice in IVF laboratories. Human Reproduction. 2016.
- ESHRE. Good practice recommendations on add-ons in reproductive medicine. Human Reproduction. 2023;38(11):2062–2104.
- Local and national regulations on witnessing and embryo transfer documentation.